Cancer types
Colorectal Cancer
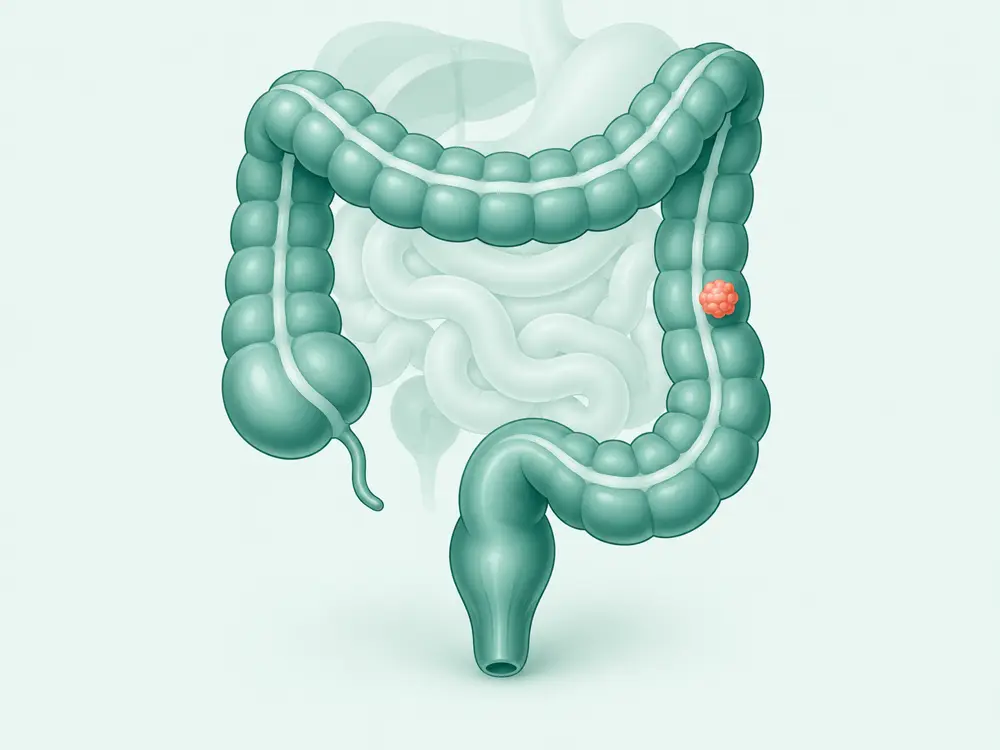
Colorectal cancer covers cancers of the colon and rectum, with RAS, BRAF, MSI/MMR, and HER2 status shaping systemic treatment options.
Not a diagnosis and not final medical advice. Must be reviewed by a doctor.
What is most important to know?
Most colorectal cancers originate from adenocarcinoma which develops from polyps in the intestinal wall.
Molecular status is particularly important: RAS and BRAF status influence whether the anti-EGFR antibody category is relevant, while MSI/MMR status opens up the immunotherapy category in some patients.
Liver or lung involvement in advanced stages is often part of the discussion, including the possibility of local treatment for limited lesions.
Colorectal cancer is one of the most frequently diagnosed cancers in the world, and the number of cases at a younger age is reported to be increasing in several countries. Specific figures are not shown without direct quotation.
Tumour location and biomarkers both matter.
Commonly discussed symptoms
- Persistent changes in bowel patterns.
- Blood in the stool or black stool.
- Stomach pain or cramps.
- Weight loss and fatigue due to anemia.
- Feeling of incompleteness after defecation.
These symptoms are not specific. A doctor still needs to assess the cause.
Risk factors
- Older age.
- Previous history of adenoma polyps or colorectal cancer.
- Family history and certain genetic conditions such as Lynch syndrome.
- Lifestyle factors include diet and physical activity levels.
What shapes the options?
Treatment discussions usually follow this path. The more complete each step is, the more focused the discussion with your doctor becomes.
Diagnosis
Confirmed through pathology review.
Subtype
3 subtypes discussed on this page.
Stage
Staging uses the TNM system which assesses the depth of intestinal wall invasion, lymph node involvement, and distant spread.
Biomarkers
Relevant markers: KRAS, BRAF, MSI / MMR, HER2, NTRK.
Treatment history
Each previous line affects the next option.
Progression?
If the disease progresses, reassessment and molecular testing are usually discussed.
Next step
Further evaluation, clinical trials, or a second opinion.
Stage I
Tumour limited to the bowel lining without spread to lymph nodes.
Stage II
Tumour has penetrated the bowel wall without lymph node involvement.
Stage III
Lymph nodes around the bowel are involved.
Stage IV
There is spread to another organ such as the liver or lung.
Relevant biomarkers
Molecular testing shapes categories, not decisions
KRAS
KRAS is a gene that regulates growth signals.
Next-generation sequencing (NGS) · KRAS PCR
View biomarker →BRAF
BRAF is a gene that regulates cell growth signals.
Next-generation sequencing (NGS) · BRAF PCR
View biomarker →HER2
HER2 is a protein on the surface of cells that can promote growth.
Immunohistochemistry (IHC) · FISH (fluorescence in situ hybridisation)
View biomarker →NTRK
NTRK fusion is a change that combines the NTRK gene with another gene.
Next-generation sequencing (NGS) · Immunohistochemistry (IHC)
View biomarker →
Progression and resistance concepts
- Progression can occur locally, regionally, or through spread to the liver, lungs, and stomach lining.
- Molecular status may change after therapy, so reexamination of new tissue is sometimes considered.
- In diseases with lesions limited to the liver, discussions often include the possibility of surgery or local treatment of the lesions.
- Subsequent choices consider regimen history, tolerance to previous therapy, and availability of clinical trials.
What is usually checked?
The pathology report needs to state the histological type, grade, MSI/MMR status, and RAS and BRAF status when examined. This status determines whether anti-EGFR antibodies are relevant for discussion.
Colonoscopy
A flexible-camera examination of the whole colon, with tissue sampling when an abnormality is found.
Tumour tissue biopsy
Collection of tumour tissue to confirm the diagnosis and provide material for further testing.
Immunohistochemistry (IHC)
A test that uses antibodies to mark specific proteins in tumour tissue.
KRAS PCR
A focused test for specific changes in the KRAS gene.
BRAF PCR
A focused test for changes in the BRAF gene.
MSI PCR
A molecular test to assess microsatellite instability.
Next-generation sequencing (NGS)
A test that reads many genes from one tumour sample to find actionable changes.
CT scan
Cross-sectional imaging to assess tumour size, location, and nearby organs.
MRI
Magnetic-field imaging that is especially useful for soft tissue, brain, and spine assessment.
PET-CT
Combined imaging that shows metabolic activity and anatomical location.
Treatment options commonly discussed
The actual order and combination are always determined by the team directly examining the patient.
Surgery (oncologic surgery)
Removal of a tumour through surgery, often part of a plan intended to cure early-stage solid cancers.
Learn
Chemotherapy
Systemic cytotoxic drugs that act on rapidly dividing cells, given in scheduled cycles.
Learn
Radiotherapy
Use of directed radiation to kill or control cancer cells in a specific area.
Learn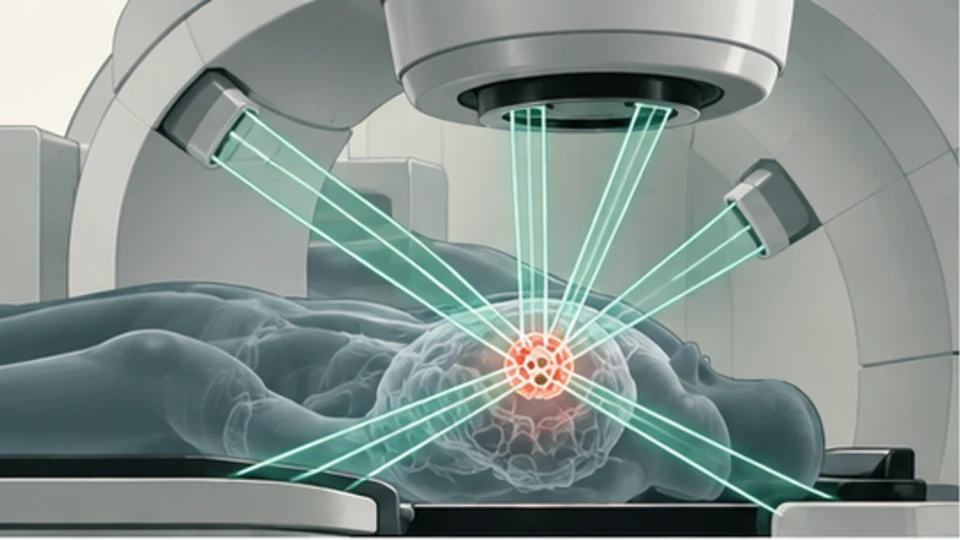
Precision radiotherapy (IMRT and VMAT)
Intensity-modulated radiotherapy that shapes the dose to the tumour contour so nearby healthy tissue is better protected.
Learn
Targeted therapy
Drugs that act on a specific molecular marker in cancer cells, selected based on biomarker test results.
Learn
Immunotherapy
Treatment that helps the immune system recognise and attack cancer cells, usually through immune checkpoint inhibitors.
Learn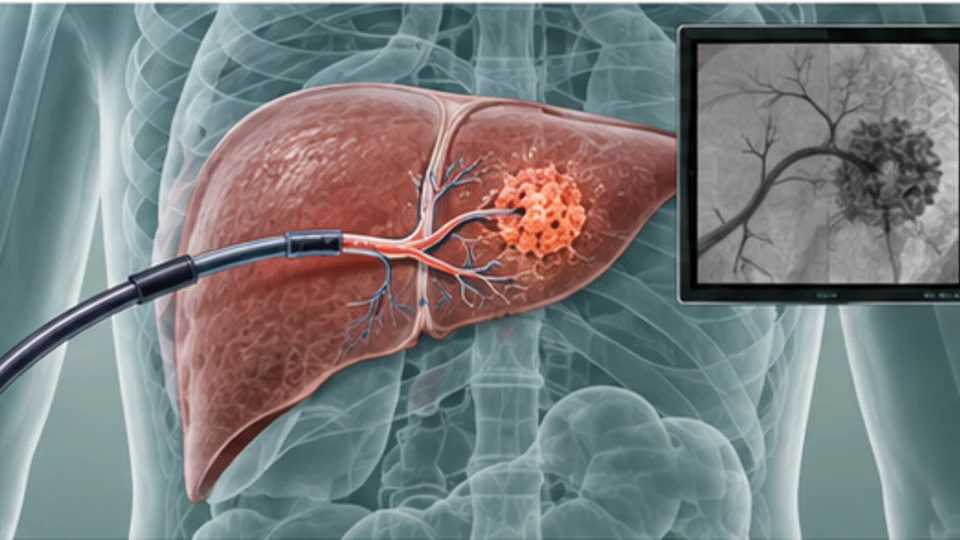
Oncology intervention (interventional radiology)
Minimally invasive image-guided procedures for diagnosis, local therapy, or complication management.
Learn
Supportive and palliative care
Management of symptoms, pain, and daily needs alongside cancer treatment.
LearnWhen are clinical trials discussed?
Trial group and treatment history
Clinical trials are usually discussed after standard pathways are mapped, or when biomarker results point to a specifically studied group. There are currently 0 registry records related to Colorectal cancer, and 0 mention a specific biomarker.
NO DATA
No studies were filtered for this cancer group in the latest registry data.
What should be prepared for a second opinion?
Records usually requested
- Latest colonoscopy and pathology reports.
- RAS, BRAF, MSI/MMR, and HER2 examination results.
- Recent CT scan of the chest, abdomen, and pelvis.
- Records of previous operations along with pathology reports.
- Note the chemotherapy regimen that has been undertaken and the response.
Questions for the oncologist
- Have my RAS, BRAF, MSI/MMR and HER2 status been completely checked?
- How does this molecular status change my therapeutic options?
- Can lesions in the liver or lungs still be treated with local measures?
- Do I need genetic testing to assess family risk?
- Are there any clinical trials that match my markers?
Have KRAS and BRAF been tested in your case?
Not sure about the next step for Colorectal cancer?
Build a case summary so your documents and questions are organised before choosing the next step. This is what happens after you upload.
Upload reports
Photos or PDFs of pathology, biomarkers, imaging and treatment history.
Case structured
Documents are turned into a structured case summary.
Navigator review
A human navigator checks completeness before anything is shared.
Provider review
With your consent, the case is discussed with providers for assessment and a written quote.
Not sure about the next step for Colorectal cancer?
Build a case summary so your documents and questions are organised before choosing the next step.
After submission, a human navigator reviews your request and contacts you through your chosen channel. The WhatsApp message already includes this page context, so you do not need to explain from the beginning.
Clinical data is not requested in the form and is not sent to analytics. Do not send medical reports through WhatsApp or email; use the secure upload page. We do not promise eligibility or any treatment outcome.
Deeper references
A reference section for readers who want details on subtypes, drugs, or every study record.
Colon adenocarcinoma
Draft, not yet medically reviewedThe most common form in the colon, developing from the inner lining of the bowel wall.
RAS and BRAF status determine whether anti-EGFR antibodies are relevant. MSI/MMR status determines whether immunotherapy is considered.
Colorectal cancer with DNA repair deficiency (dMMR or MSI-high)
Draft, not yet medically reviewedA group with DNA repair deficiency that opens an immunotherapy category and requires consideration of genetic risk.
Tumors with dMMR have many genetic changes so they are easier for the immune system to recognize. This condition may also be associated with Lynch syndrome affecting familial risk.
Relevant markers
Stage note
Staging still uses the TNM system, but dMMR status adds its own consideration in the choice of systemic therapy.
Rectal adenocarcinoma
Draft, not yet medically reviewedCancer in the final part of the large bowel, with special considerations around pelvic function and treatment sequence.
The location of the tumor in the pelvis means that treatment planning takes into account surrounding organs such as the sphincter and bladder, and radiotherapy is often used before surgery.
You just read about Colorectal cancer. Next:
KRAS
KRAS is a gene that regulates growth signals.
BRAF
BRAF is a gene that regulates cell growth signals.
Understanding clinical trials: terms, phases, and how to check early fit
7 min read
Preparing medical records for a second opinion or clinical trial
6 min read
Clinical trials related to Colorectal cancer
0 public registry records filtered for this group.
Upload Medical Reports
Build a case summary so your documents and questions are organised.
Next steps
These suggestions come from links between entries in TanyaKanker's database, not from a medical judgement. Each suggestion includes why it appears.
Next to learn
- BRAF
Biomarker
Reason: Related through a biomarker
- HER2
Biomarker
Reason: Related through a biomarker
- Why stage 4 is not one single disease
Explainer
Reason: Related to this page
- BRAF V600E
Molecular alteration
Reason: Related to this page
- KRAS G12C
Molecular alteration
Reason: Related to this page
- Cancer treatment costs and financing: how to frame the questions
Guide
Reason: Related to this page
To check
- Tumour tissue biopsy
Diagnostic test
Reason: Memerlukan pemeriksaan
- CT scan
Diagnostic test
Reason: Memerlukan pemeriksaan
- Immunohistochemistry (IHC)
Diagnostic test
Reason: Memerlukan pemeriksaan
- Colonoscopy
Diagnostic test
Reason: Memerlukan pemeriksaan
- MRI
Diagnostic test
Reason: Memerlukan pemeriksaan
- Next-generation sequencing (NGS)
Diagnostic test
Reason: Memerlukan pemeriksaan
What you can do
- Upload medical reports
Build a case summary in twelve steps
Reason: Often the most useful next step after reading this page
- Request a second opinion
Review of the treatment plan
Reason: Relevant when a treatment plan is being considered
- Consult a navigator
A request is recorded with this page context
Reason: For asking the next step directly
Recently updated
- Leukemia
Cancer page
Date: Data revision 2026-09-10
- Brain Cancer
Cancer page
Date: Data revision 2026-09-10
- Pancreatic Cancer
Cancer page
Date: Data revision 2026-09-10
- Testing Osimertinib as a Treatment for Lung Cancers With an EGFR Exon 20 Change
NCT03191149 - Phase 2
Date: Registry update in the last 30 days (2026-10-15)
Want to follow changes on this topic? Save the page or follow the topic so it is easy to find again. View saved items.

Prepare for your next consultation
Use the free six-question tool to prepare questions for your doctor.