Cancer types
Breast Cancer
Breast cancer is classified mainly by hormone-receptor and HER2 status, and that classification determines the direction of systemic treatment discussion.
Not a diagnosis and not final medical advice. Must be reviewed by a doctor.
What is most important to know?
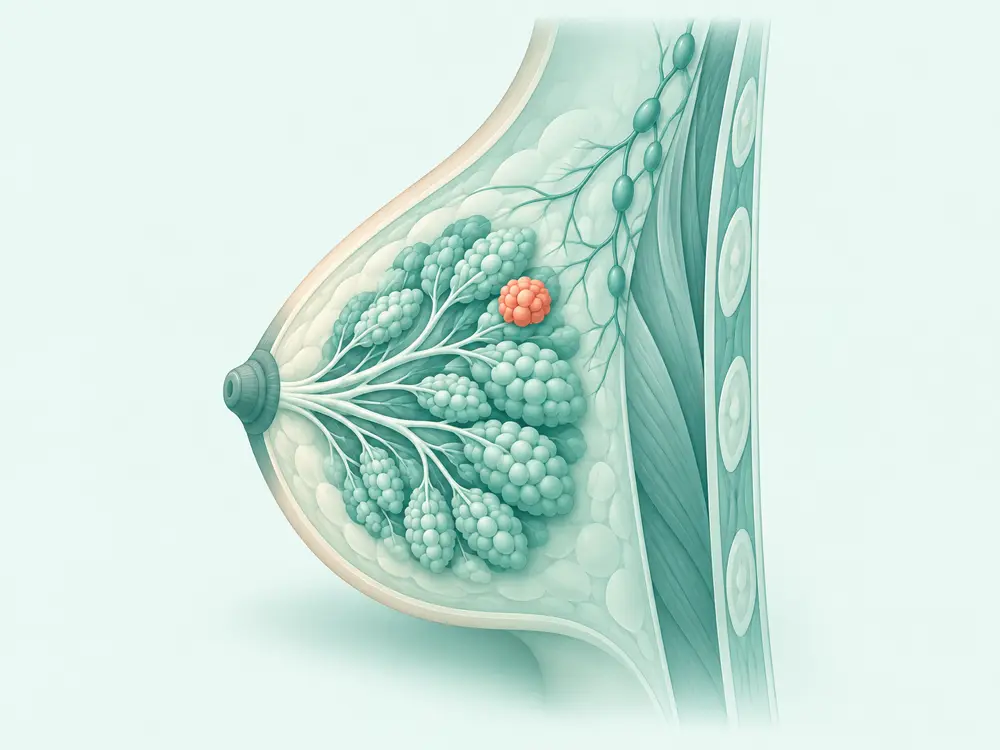
Breast cancer originates from glandular tissue or ducts in the breast. Pathological examination determines the cell type and markers that determine the therapeutic category.
The three large groups that are often discussed are hormone receptor positive with HER2 negative, HER2 positive, and triple negative, that is, without hormone receptors or HER2.
The triple negative group requires discussion of other markers such as PD-L1 and BRCA, and in some cases consideration of clinical trials.
Breast cancer is one of the cancers with the highest number of cases in women in many countries, including Indonesia. Specific figures are not shown without direct quotation.
Receptor status shapes systemic options.
Commonly discussed symptoms
- Painless lump in the breast or armpit.
- Changes in the shape, curve, or skin of the breast that resemble orange peel.
- Discharge from the nipple, especially if it is bloody.
- Changes in the nipples such as being pulled inward.
- Persistent pain in one area.
These symptoms are not specific. A doctor still needs to assess the cause.
Risk factors
- Older age and family history in some cases.
- Inherited changes in genes such as BRCA1 or BRCA2.
- History of chest radiation at a young age.
- Hormonal factors such as age of first menstruation and age of menopause.
What shapes the options?
Treatment discussions usually follow this path. The more complete each step is, the more focused the discussion with your doctor becomes.
Diagnosis
Confirmed through pathology review.
Subtype
3 subtypes discussed on this page.
Stage
Staging uses the TNM system which combines tumor size, lymph node involvement, and distant spread.
Biomarkers
Relevant markers: HER2, BRCA1 / BRCA2, PD-L1.
Treatment history
Each previous line affects the next option.
Progression?
If the disease progresses, reassessment and molecular testing are usually discussed.
Next step
Further evaluation, clinical trials, or a second opinion.
Stage I
A small tumour without meaningful lymph node involvement.
Stage II
A larger tumour or involvement of lymph nodes in the armpit.
Stage III
Locally advanced tumour, including wider node involvement or skin and chest wall involvement.
Stage IV
Cancer has spread to other organs such as bone, liver, lung, or brain.
Relevant biomarkers
Molecular testing shapes categories, not decisions
HER2
HER2 is a protein on the surface of cells that can promote growth.
Immunohistochemistry (IHC) · FISH (fluorescence in situ hybridisation)
View biomarker →BRCA1 / BRCA2
BRCA1 and BRCA2 are genes that play a role in repairing DNA damage.
Next-generation sequencing (NGS) · Tumour tissue biopsy
View biomarker →PD-L1
PD-L1 is a protein that can help cancer cells evade the immune system.
PD-L1 immunohistochemistry · Tumour tissue biopsy
View biomarker →
Progression and resistance concepts
- Progression can occur locally, regionally, or as spread to other organs. The location of spread influences the discussion of therapy.
- Hormone receptor and HER2 status may change after therapy, so repeat sampling is sometimes considered in relapsed disease.
- In HER2 positive breast cancer, the appearance of lesions in the brain is part of the discussion because it influences the choice and sequence of therapy.
- The next choice usually takes into account the disease-free interval, therapy history, and the patient's general condition.
What is usually checked?
The pathology report needs to state the histological type, grade, estrogen and progesterone receptor status, HER2 score with confirmation results if necessary, as well as PD-L1 status in the triple negative group.
Mammography
Special breast X-ray imaging to find abnormalities that are not yet palpable.
Image-guided breast biopsy
Collection of breast tissue guided by ultrasound or X-ray to confirm the diagnosis.
Immunohistochemistry (IHC)
A test that uses antibodies to mark specific proteins in tumour tissue.
FISH (fluorescence in situ hybridisation)
A test that detects changes in the number or arrangement of genetic material in tumour cells.
Next-generation sequencing (NGS)
A test that reads many genes from one tumour sample to find actionable changes.
PD-L1 immunohistochemistry
A staining test to assess PD-L1 expression and its score.
CT scan
Cross-sectional imaging to assess tumour size, location, and nearby organs.
PET-CT
Combined imaging that shows metabolic activity and anatomical location.
MRI
Magnetic-field imaging that is especially useful for soft tissue, brain, and spine assessment.
Treatment options commonly discussed
The actual order and combination are always determined by the team directly examining the patient.
Surgery (oncologic surgery)
Removal of a tumour through surgery, often part of a plan intended to cure early-stage solid cancers.
Learn
Radiotherapy
Use of directed radiation to kill or control cancer cells in a specific area.
Learn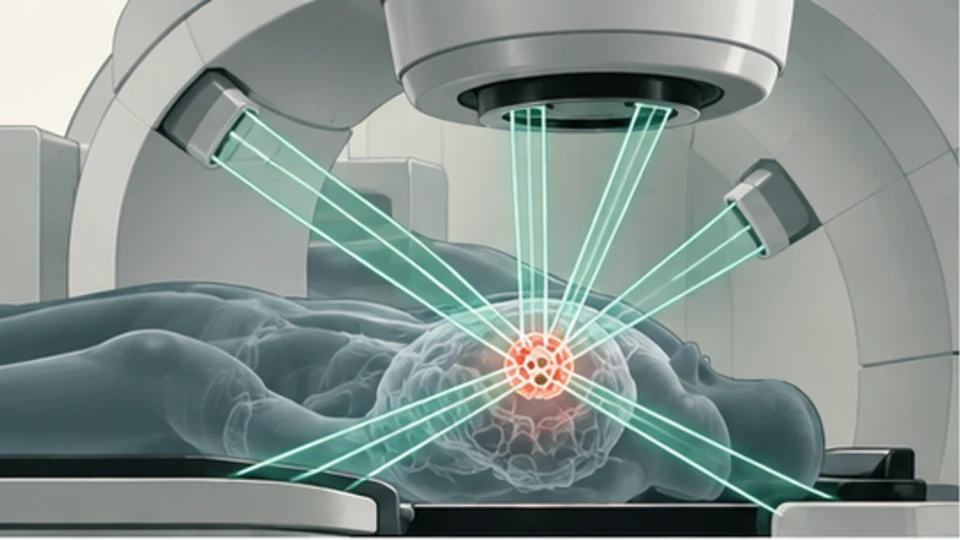
Precision radiotherapy (IMRT and VMAT)
Intensity-modulated radiotherapy that shapes the dose to the tumour contour so nearby healthy tissue is better protected.
Learn
Chemotherapy
Systemic cytotoxic drugs that act on rapidly dividing cells, given in scheduled cycles.
Learn
Targeted therapy
Drugs that act on a specific molecular marker in cancer cells, selected based on biomarker test results.
Learn
Immunotherapy
Treatment that helps the immune system recognise and attack cancer cells, usually through immune checkpoint inhibitors.
Learn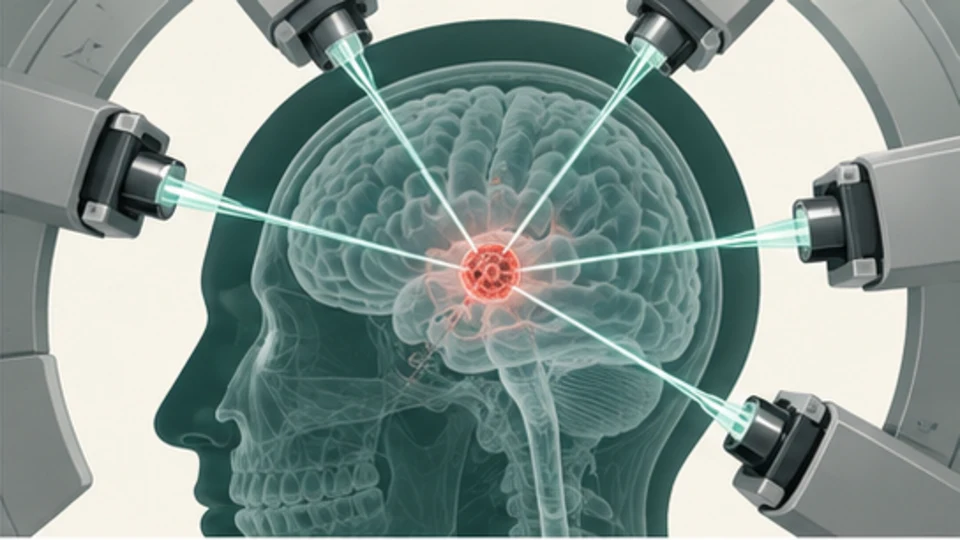
SRS (intracranial stereotactic radiotherapy)
High-dose, high-precision radiotherapy for lesions in the brain, usually in one or a few sessions.
Learn
Supportive and palliative care
Management of symptoms, pain, and daily needs alongside cancer treatment.
LearnWhen are clinical trials discussed?
Trial group and treatment history
Clinical trials are usually discussed after standard pathways are mapped, or when biomarker results point to a specifically studied group. There are currently 0 registry records related to Breast cancer, and 0 mention a specific biomarker.
NO DATA
No studies were filtered for this cancer group in the latest registry data.
What should be prepared for a second opinion?
Records usually requested
- The most recent pathology report included receptor status and HER2 score.
- PD-L1 and BRCA examination results if available.
- Recent imaging includes bone or brain imaging if there are complaints.
- Records of previous therapy, including hormonal therapy.
- Records of previous operations and radiotherapy along with reports.
Questions for the oncologist
- What is my hormone receptor and HER2 status, and how does that change therapy options?
- Have PD-L1 scores and BRCA status been checked if relevant?
- Do I need genetic testing and counseling for family risks?
- What therapy have I had and are there any options afterward that are worth discussing?
- Is there a clinical trial that fits my marker group?
Have HER2 and BRCA1 / BRCA2 been tested in your case?
Not sure about the next step for Breast cancer?
Build a case summary so your documents and questions are organised before choosing the next step. This is what happens after you upload.
Upload reports
Photos or PDFs of pathology, biomarkers, imaging and treatment history.
Case structured
Documents are turned into a structured case summary.
Navigator review
A human navigator checks completeness before anything is shared.
Provider review
With your consent, the case is discussed with providers for assessment and a written quote.
Not sure about the next step for Breast cancer?
Build a case summary so your documents and questions are organised before choosing the next step.
After submission, a human navigator reviews your request and contacts you through your chosen channel. The WhatsApp message already includes this page context, so you do not need to explain from the beginning.
Clinical data is not requested in the form and is not sent to analytics. Do not send medical reports through WhatsApp or email; use the secure upload page. We do not promise eligibility or any treatment outcome.
Deeper references
A reference section for readers who want details on subtypes, drugs, or every study record.
Hormone-receptor-positive, HER2-negative breast cancer
Draft, not yet medically reviewedThe most common breast cancer group, with estrogen and/or progesterone receptors positive and HER2 negative.
Tumor growth depends on hormonal signals, so hormonal therapy is a major part of the discussion at many stages. Anti-HER2 antibodies are not relevant in this group.
Relevant markers
Stage note
In addition to TNM staging, the discussion often considers the risk of recurrence to determine whether additional therapy after surgery is necessary.
HER2-positive breast cancer
Draft, not yet medically reviewedA group with HER2 expression or amplification that opens antibody and antibody-drug conjugate categories.
HER2 signaling drives tumor growth. The development of anti-HER2 drugs has changed the behavior of the disease at all stages discussed.
Triple-negative breast cancer
Draft, not yet medically reviewedA group without hormone receptors or HER2, so hormonal therapy and anti-HER2 therapy are not options.
Treatment relies on chemotherapy, immunotherapy in the PD-L1 positive group, as well as therapies targeting DNA repair weaknesses in patients with BRCA alterations.
Relevant markers
Stage note
Because systemic options are more limited, clinical trials are often part of the discussion at a later stage.
You just read about Breast cancer. Next:
HER2
HER2 is a protein on the surface of cells that can promote growth.
BRCA1 / BRCA2
BRCA1 and BRCA2 are genes that play a role in repairing DNA damage.
Understanding clinical trials: terms, phases, and how to check early fit
7 min read
Preparing medical records for a second opinion or clinical trial
6 min read
Clinical trials related to Breast cancer
0 public registry records filtered for this group.
Upload Medical Reports
Build a case summary so your documents and questions are organised.
Next steps
These suggestions come from links between entries in TanyaKanker's database, not from a medical judgement. Each suggestion includes why it appears.
Next to learn
- Breast cancer progression after HER2 therapy
Decision situation
Reason: Has a decision situation
- Lung cancer with spread to the brain
Decision situation
Reason: Has a decision situation
- BRCA1 / BRCA2
Biomarker
Reason: Related through a biomarker
- HER2
Biomarker
Reason: Related through a biomarker
- Why treatment guidelines differ between countries
Explainer
Reason: Related to this page
- Why stage 4 is not one single disease
Explainer
Reason: Related to this page
To check
- Image-guided breast biopsy
Diagnostic test
Reason: Memerlukan pemeriksaan
- CT scan
Diagnostic test
Reason: Memerlukan pemeriksaan
- FISH (fluorescence in situ hybridisation)
Diagnostic test
Reason: Memerlukan pemeriksaan
- Immunohistochemistry (IHC)
Diagnostic test
Reason: Memerlukan pemeriksaan
- Mammography
Diagnostic test
Reason: Memerlukan pemeriksaan
- MRI
Diagnostic test
Reason: Memerlukan pemeriksaan
What you can do
- Upload medical reports
Build a case summary in twelve steps
Reason: Often the most useful next step after reading this page
- Request a second opinion
Review of the treatment plan
Reason: Relevant when a treatment plan is being considered
- Consult a navigator
A request is recorded with this page context
Reason: For asking the next step directly
Recently updated
- Leukemia
Cancer page
Date: Data revision 2026-09-10
- Brain Cancer
Cancer page
Date: Data revision 2026-09-10
- Pancreatic Cancer
Cancer page
Date: Data revision 2026-09-10
- Testing Osimertinib as a Treatment for Lung Cancers With an EGFR Exon 20 Change
NCT03191149 - Phase 2
Date: Registry update in the last 30 days (2026-10-15)
Want to follow changes on this topic? Save the page or follow the topic so it is easy to find again. View saved items.

Prepare for your next consultation
Use the free six-question tool to prepare questions for your doctor.