Cancer types
Lung Cancer
Lung cancer is divided into non-small-cell and small-cell groups, with molecular markers that strongly shape which treatment options are discussed.
Not a diagnosis and not final medical advice. Must be reviewed by a doctor.
What is most important to know?
Lung cancer occurs when cells in lung tissue grow uncontrollably. Most cases are grouped into non-small-cell lung cancer and small-cell lung cancer.
These group differences are important because they influence the direction of investigations, the order of therapy, and the types of clinical trials that may be appropriate.
Examination of molecular markers in advanced non-small cell lung cancer is generally part of the initial planning, as the results may change the category of therapy being discussed.
Lung cancer is one of the most frequently diagnosed cancers in the world and is among the largest disease burdens in Indonesia. Specific incidence figures are not shown on this page because the source needs to be cited directly.
Lung cancer is not one disease.
Commonly discussed symptoms
- Persistent or changing cough.
- Shortness of breath or chest pain.
- Coughing up blood.
- Weight loss for no apparent reason.
- Hoarseness or recurrent lung infections.
- Fatigue that does not improve with rest.
These symptoms are not specific. A doctor still needs to assess the cause.
Risk factors
- History of smoking, including e-cigarettes and smoke exposure.
- Exposure to asbestos, radon, or carcinogens in the workplace.
- Family history of lung cancer in some cases.
- History of chronic lung disease and certain infections.
What shapes the options?
Treatment discussions usually follow this path. The more complete each step is, the more focused the discussion with your doctor becomes.
Diagnosis
Confirmed through pathology review.
Subtype
4 subtypes discussed on this page.
Stage
Staging uses the TNM system (tumor size, lymph node involvement, and distant spread). Small cell lung cancer is also often grouped into limited and extensive stages.
Biomarkers
Relevant markers: EGFR, ALK, ROS1, KRAS, MET, RET, BRAF, HER2, NTRK, PD-L1.
Treatment history
Each previous line affects the next option.
Progression?
If the disease progresses, reassessment and molecular testing are usually discussed.
Next step
Further evaluation, clinical trials, or a second opinion.
Stage I
Tumour limited to the lung without lymph node involvement.
Stage II
A larger tumour or involvement of lymph nodes near the lung.
Stage III
Tumour involvement of lymph nodes in the chest, often divided into IIIA, IIIB, and IIIC.
Stage IV
Cancer has spread outside the chest cavity or to another organ.
Relevant biomarkers
Molecular testing shapes categories, not decisions

Visual explainer
The EGFR biomarker journey
From an EGFR-positive result and targeted therapy options to what is commonly checked when treatment stops working.
View the EGFR explainer
EGFR
EGFR is a gene that regulates cell growth signals.
Next-generation sequencing (NGS) · EGFR PCR
View biomarker →ALK
ALK fusion occurs when two genes fuse and produce abnormal growth signals.
ALK immunohistochemistry · FISH (fluorescence in situ hybridisation)
View biomarker →ROS1
ROS1 is a gene that, when fused with other genes, can encourage the growth of cancer cells.
Next-generation sequencing (NGS) · ALK immunohistochemistry
View biomarker →KRAS
KRAS is a gene that regulates growth signals.
Next-generation sequencing (NGS) · KRAS PCR
View biomarker →MET
MET is a gene involved in cell growth signaling.
Next-generation sequencing (NGS) · FISH (fluorescence in situ hybridisation)
View biomarker →RET
RET fusion occurs when the RET gene fuses with another gene.
Next-generation sequencing (NGS) · FISH (fluorescence in situ hybridisation)
View biomarker →BRAF
BRAF is a gene that regulates cell growth signals.
Next-generation sequencing (NGS) · BRAF PCR
View biomarker →HER2
HER2 is a protein on the surface of cells that can promote growth.
Immunohistochemistry (IHC) · FISH (fluorescence in situ hybridisation)
View biomarker →NTRK
NTRK fusion is a change that combines the NTRK gene with another gene.
Next-generation sequencing (NGS) · Immunohistochemistry (IHC)
View biomarker →PD-L1
PD-L1 is a protein that can help cancer cells evade the immune system.
PD-L1 immunohistochemistry · Tumour tissue biopsy
View biomarker →
Progression and resistance concepts
- Progression means the disease gets bigger or appears in new locations despite ongoing therapy.
- Resistance can occur because tumor cells change so that signals that were previously inhibited become active again through other pathways.
- In lung cancer with target markers, repeat tissue or blood tests are often considered when progression occurs.
- Discussions about next steps usually consider the patient's general condition, existing therapies, and clinical trial options.
What is usually checked?
Histological examination determines whether the tumor is adenocarcinoma, squamous cell carcinoma, large cell carcinoma, or small cell. This conclusion determines the type of molecular examination that makes sense to perform.
Tumour tissue biopsy
Collection of tumour tissue to confirm the diagnosis and provide material for further testing.
Immunohistochemistry (IHC)
A test that uses antibodies to mark specific proteins in tumour tissue.
Next-generation sequencing (NGS)
A test that reads many genes from one tumour sample to find actionable changes.
EGFR PCR
A focused test that looks for specific changes in the EGFR gene.
ALK immunohistochemistry
A staining test to detect ALK protein in tumour tissue.
PD-L1 immunohistochemistry
A staining test to assess PD-L1 expression and its score.
Liquid biopsy (ctDNA)
A blood test that looks for tumour genetic material to supplement or partly replace tissue testing.
CT scan
Cross-sectional imaging to assess tumour size, location, and nearby organs.
PET-CT
Combined imaging that shows metabolic activity and anatomical location.
MRI
Magnetic-field imaging that is especially useful for soft tissue, brain, and spine assessment.
Spirometry (lung function)
A lung function test to assess breathing capacity before certain procedures.
Treatment options commonly discussed
The actual order and combination are always determined by the team directly examining the patient.
Surgery (oncologic surgery)
Removal of a tumour through surgery, often part of a plan intended to cure early-stage solid cancers.
Learn
Radiotherapy
Use of directed radiation to kill or control cancer cells in a specific area.
Learn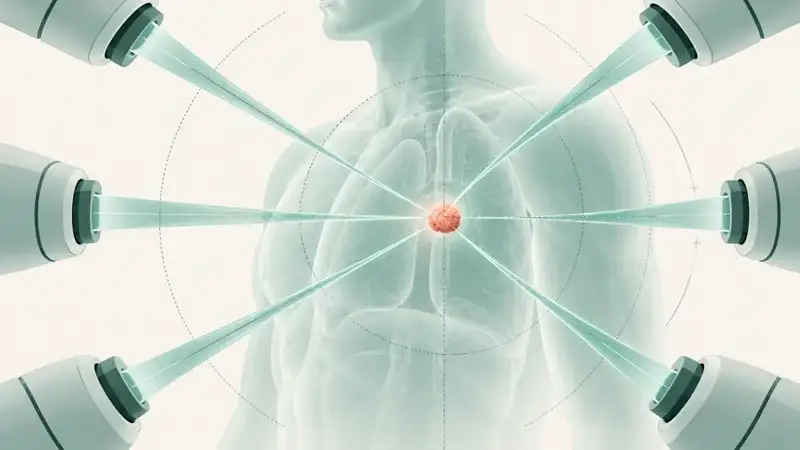
SBRT (stereotactic radiotherapy)
Highly targeted high-dose radiotherapy delivered in a small number of sessions to a small, clear target.
Learn
Chemotherapy
Systemic cytotoxic drugs that act on rapidly dividing cells, given in scheduled cycles.
Learn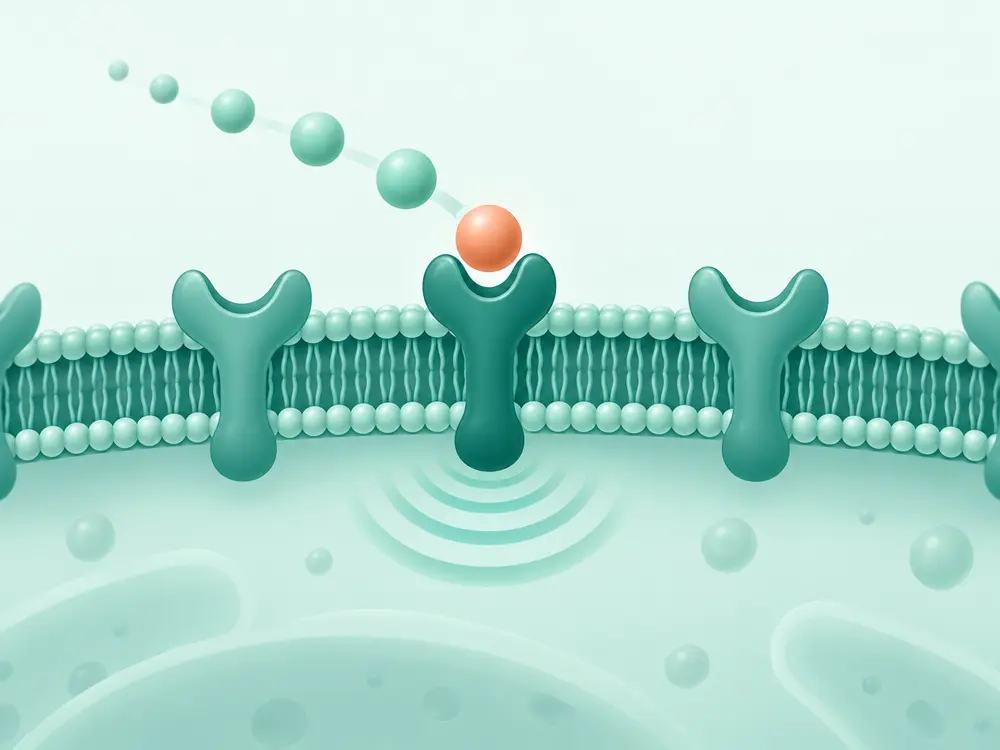
Targeted therapy
Drugs that act on a specific molecular marker in cancer cells, selected based on biomarker test results.
Learn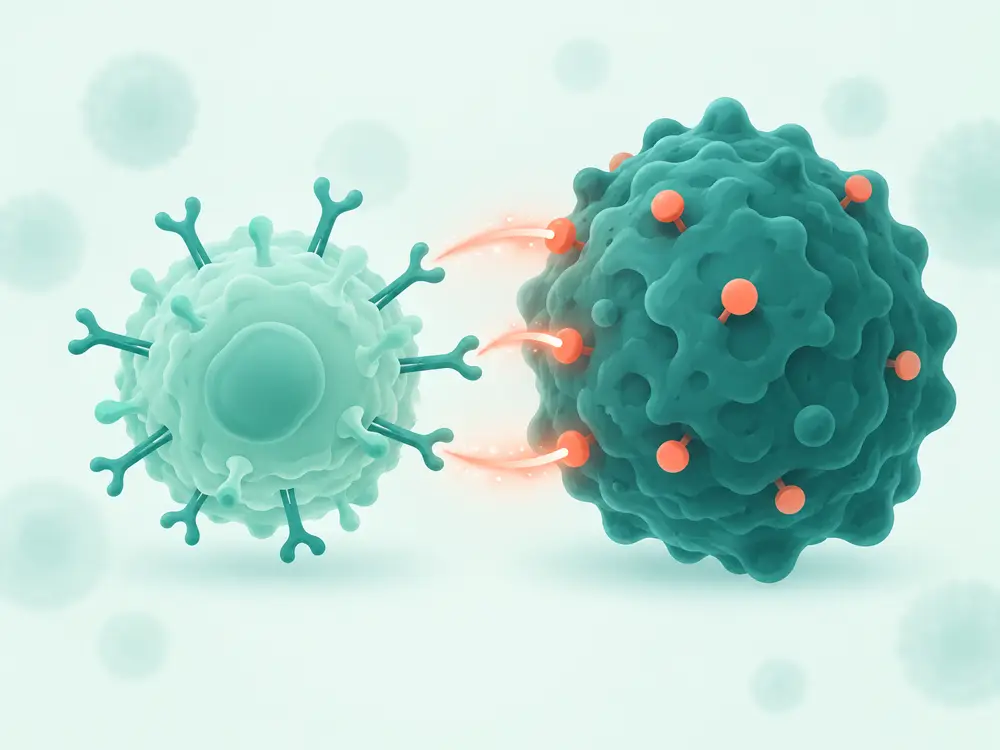
Immunotherapy
Treatment that helps the immune system recognise and attack cancer cells, usually through immune checkpoint inhibitors.
Learn
Supportive and palliative care
Management of symptoms, pain, and daily needs alongside cancer treatment.
LearnWhen are clinical trials discussed?
Trial group and treatment history
Clinical trials are usually discussed after standard pathways are mapped, or when biomarker results point to a specifically studied group. There are currently 80 registry records related to Lung cancer, and 33 mention a specific biomarker.
NCT03191149Phase 2Targeted therapy
Testing Osimertinib as a Treatment for Lung Cancers With an EGFR Exon 20 Change
Lung Cancer | biomarker: EGFR | Targeted therapy
United States347 registry sites
Why this appears: Appears because it is recorded for Lung Cancer, it mentions marker EGFR, the treatment category is Targeted therapy.
What to verify: Acceptance of patients from outside the local country has not been verified.
- Registry
- Recruiting in registry
- Site
- Not verified
- International access
- Unknown
- Patient match
- Not assessed
Last checked 16 Oktober 2026Source ClinicalTrials.govNCT03191149Not verified
NCT03460977Phase 1Combination regimen
A Study of Mevrometostat for Treatment of Relapsed/Refractory SCLC, Castration Resistant Prostate Cancer, and Follicular Lymphoma
United States, Bulgaria, China +584 registry sites
Why this appears: Appears because it is recorded for Lung Cancer.
What to verify: Acceptance of patients from outside the local country has not been verified.
- Registry
- Recruiting in registry
- Site
- Not verified
- International access
- Unknown
- Patient match
- Not assessed
Last checked 16 Oktober 2026Source ClinicalTrials.govNCT03460977Not verified
NCT04267848Phase 3Immunotherapy
Testing the Addition of a Type of Drug Called Immunotherapy to the Usual Chemotherapy Treatment for Non-small Cell Lung Cancer, an ALCHEMIST Treatment Trial (Chemo-IO [ACCIO])
Lung Cancer | Immunotherapy, Chemotherapy
United States, Guam1151 registry sites
Why this appears: Appears because it is recorded for Lung Cancer, the treatment category is Immunotherapy.
What to verify: Acceptance of patients from outside the local country has not been verified.
- Registry
- Recruiting in registry
- Site
- Not verified
- International access
- Unknown
- Patient match
- Not assessed
Last checked 16 Oktober 2026Source ClinicalTrials.govNCT04267848Not verified
NCT05636969Not applicableCombination regimen
Multimodal Prehabilitation in Patients With Lung Cancer Undergoing Neoadjuvant Therapy
Spain1 registry sites
Why this appears: Appears because it is recorded for Lung Cancer.
What to verify: Acceptance of patients from outside the local country has not been verified.
- Registry
- Recruiting in registry
- Site
- Not verified
- International access
- Unknown
- Patient match
- Not assessed
Last checked 16 Oktober 2026Source ClinicalTrials.govNCT05636969Not verified
What should be prepared for a second opinion?
Records usually requested
- Complete pathology report including histology type.
- Molecular examination report (panel or single) along with methods and laboratories.
- PD-L1 immunohistochemistry results with clear score types.
- Recent imaging results (CT, PET-CT, and brain MRI if available).
- Records of therapy that has been undertaken including dates and responses.
Questions for the oncologist
- Which group does my lung cancer belong to, and what is the basis for determining this from the pathology report?
- What marker examinations have been carried out, with what methods, and what are the complete results?
- Is it necessary to check additional markers before selecting the next plan?
- What is the goal of the proposed therapy: cure, prolong disease control, or reduce symptoms?
- How will success be assessed and by what checks?
- Are there any clinical trials that might match my markers and therapy history?
Does your result show EGFR, ALK or another biomarker?
Not sure about the next step for Lung cancer?
Build a case summary so your documents and questions are organised before choosing the next step. This is what happens after you upload.
Upload reports
Photos or PDFs of pathology, biomarkers, imaging and treatment history.
Case structured
Documents are turned into a structured case summary.
Navigator review
A human navigator checks completeness before anything is shared.
Provider review
With your consent, the case is discussed with providers for assessment and a written quote.
Not sure about the next step for Lung cancer?
Build a case summary so your documents and questions are organised before choosing the next step.
After submission, a human navigator reviews your request and contacts you through your chosen channel. The WhatsApp message already includes this page context, so you do not need to explain from the beginning.
Clinical data is not requested in the form and is not sent to analytics. Do not send medical reports through WhatsApp or email; use the secure upload page. We do not promise eligibility or any treatment outcome.
Deeper references
A reference section for readers who want details on subtypes, drugs, or every study record.
Non-small-cell lung cancer: adenocarcinoma
Draft, not yet medically reviewedThe most common non-small-cell lung cancer subtype and the one most often carrying actionable molecular markers.
Tumors originate from cells that line lung tissue and produce mucus. This group is most often associated with the discovery of markers such as EGFR, ALK, ROS1, KRAS, MET, RET, BRAF, HER2, and NTRK.
Non-small-cell lung cancer: squamous cell carcinoma
Draft, not yet medically reviewedA non-small-cell lung cancer subtype arising from squamous cells, most often located near the main airways.
These tumors often have a high mutation burden and are less likely to have target markers such as EGFR or ALK than adenocarcinomas. PD-L1 testing and molecular panels remain frequently considered.
Non-small-cell lung cancer: large cell carcinoma
Draft, not yet medically reviewedA non-small-cell lung cancer subtype that does not clearly show adenocarcinoma or squamous patterns.
This diagnosis is often established after a thorough pathological examination. Additional testing is important to confirm actionable markers and rule out other possible subtypes.
Small-cell lung cancer (SCLC)
Draft, not yet medically reviewedA fast-growing lung cancer group usually treated with chemotherapy and immunotherapy rather than surgery, except in very early stages.
SCLC rarely has target markers like adenocarcinoma. Grouping usually uses limited and extensive stage categories instead of detailed TNM in daily practice.
Relevant markers
Stage note
Limited or extensive division influences the treatment plan; Brain imaging examinations are often performed because of the risk of spread.
Frequently asked questions
Short answers to the most common questions; full explanations are in the sections above.
What is the difference between non-small cell and small cell lung cancer?
Most lung cancers are grouped as non-small cell lung cancer (NSCLC) or small cell lung cancer (SCLC). The distinction affects testing, treatment sequence, and which trials may be relevant. SCLC is also often grouped as limited or extensive stage.
Why is molecular marker testing important in lung cancer?
In advanced NSCLC, molecular marker testing is usually part of early planning because results can change which treatment categories are discussed. Histology first establishes the tumor type, and that result guides which molecular tests are sensible.
What tests are usually done?
The page discusses tissue biopsy, immunohistochemistry, molecular panels such as NGS, and CT, PET-CT, or MRI imaging. Histology determines whether the tumor is adenocarcinoma, squamous, large cell, or small cell before markers such as EGFR, ALK, and PD-L1 are assessed.
What does stage mean in lung cancer?
Staging uses the TNM system: tumor size, lymph-node involvement, and distant spread. Stage IV means cancer has spread outside the chest cavity or to another organ. Stage helps frame treatment discussion but does not describe the whole patient condition.
Which documents should be prepared for a lung cancer second opinion?
Prepare the full pathology report including histology, molecular testing report with method and laboratory, PD-L1 immunohistochemistry with score type, recent imaging, and prior-treatment notes with dates and responses. The same checklist appears in the second-opinion section of the page.
You just read about Lung cancer. Next:
EGFR
EGFR is a gene that regulates cell growth signals.
Tagrisso stopped working? Steps after osimertinib progression
10 min read
EGFR C797S
C797S changes the binding site of the drug so that ongoing therapy may lose effectiveness.
Understanding clinical trials: terms, phases, and how to check early fit
7 min read
Clinical trials related to Lung cancer
80 public registry records filtered for this group.
Upload Medical Reports
Build a case summary so your documents and questions are organised.
Related explainers
EGFR after osimertinib: fourth-generation trials are starting to report early results
No fourth-generation EGFR targeted therapy has been approved anywhere.
Why treatment guidelines differ between countries
Guidelines differ because they consider available evidence, medicine availability, regulation, and local service context.
What recruiting status means in a clinical trial registry
Recruiting status means a study is listed as seeking participants.
Why a medicine approved abroad is not automatically available in Indonesia
Regulatory approval applies to the jurisdiction that issued it.
Next steps
These suggestions come from links between entries in TanyaKanker's database, not from a medical judgement. Each suggestion includes why it appears.
Next to learn
- Lung cancer progression after targeted therapy
Decision situation
Reason: Has a decision situation
- Lung cancer progression after immunotherapy
Decision situation
Reason: Has a decision situation
- ALK
Biomarker
Reason: Related through a biomarker
- BRAF
Biomarker
Reason: Related through a biomarker
- What biomarker results do and do not say
Explainer
Reason: Related to this page
- What recruiting status means in a clinical trial registry
Explainer
Reason: Related to this page
To check
- Cabozantinib in Patients With RET Fusion-Positive Advanced Non-Small Cell Lung Cancer and Those With Other Genotypes: ROS1 or NTRK Fusions or Increased MET or AXL Activity
Clinical trial
Reason: Has a clinical trial
- Testing Osimertinib as a Treatment for Lung Cancers With an EGFR Exon 20 Change
Clinical trial
Reason: Has a clinical trial
- Dabrafenib and/or Trametinib Rollover Study
Clinical trial
Reason: Has a clinical trial
- A Study of Mevrometostat for Treatment of Relapsed/Refractory SCLC, Castration Resistant Prostate Cancer, and Follicular Lymphoma
Clinical trial
Reason: Has a clinical trial
- Biomarkers for Risk Stratification in Lung Cancer
Clinical trial
Reason: Has a clinical trial
- Osimertinib With or Without Bevacizumab as Initial Treatment for Patients With EGFR-Mutant Lung Cancer
Clinical trial
Reason: Has a clinical trial
What you can do
- Upload medical reports
Build a case summary in twelve steps
Reason: Often the most useful next step after reading this page
- Request a second opinion
Review of the treatment plan
Reason: Relevant when a treatment plan is being considered
- Consult a navigator
A request is recorded with this page context
Reason: For asking the next step directly
Recently updated
- Leukemia
Cancer page
Date: Data revision 2026-09-10
- Brain Cancer
Cancer page
Date: Data revision 2026-09-10
- Pancreatic Cancer
Cancer page
Date: Data revision 2026-09-10
- Testing Osimertinib as a Treatment for Lung Cancers With an EGFR Exon 20 Change
NCT03191149 - Phase 2
Date: Registry update in the last 30 days (2026-10-15)
Want to follow changes on this topic? Save the page or follow the topic so it is easy to find again. View saved items.

Prepare for your next consultation
Use the free six-question tool to prepare questions for your doctor.